Obesity, treated properly.
Obesity is a chronic metabolic condition, not a willpower deficit. It responds to treatment the way chronic conditions do: strongly while treated, and it tends to return when treatment stops. The evidence for medical treatment is now very good — and very specific.
What it is
Clinically, obesity is defined as a BMI of 30 or above; 27–30 with a weight-related condition (high blood pressure, insulin resistance, sleep apnea) is the threshold where medication is typically considered. BMI is a screening tool, not a verdict — it misses muscle mass and fat distribution — but it remains the number treatment decisions key off.
The biology that matters: appetite and satiety are hormonally regulated, and that regulation adapts to defend stored weight. This is why diets that rely purely on restriction show high long-term regain, and why medications that act on appetite signaling changed the field.
Who this describes
- BMI 30+, or 27+ with a weight-related condition
- Weight that returns after repeated diet cycles
- Constant food preoccupation ('food noise')
- Weight-driven conditions: prediabetes, high blood pressure, sleep apnea, joint pain
How it's diagnosed
Diagnosis is clinical: BMI plus history plus, where relevant, labs (HbA1c, lipids, thyroid). At Zappy, the intake asks for exactly this, and a U.S.-licensed clinician reviews it within 24 hours — medication is prescribed only where it's clinically appropriate.
The treatment landscape — honestly
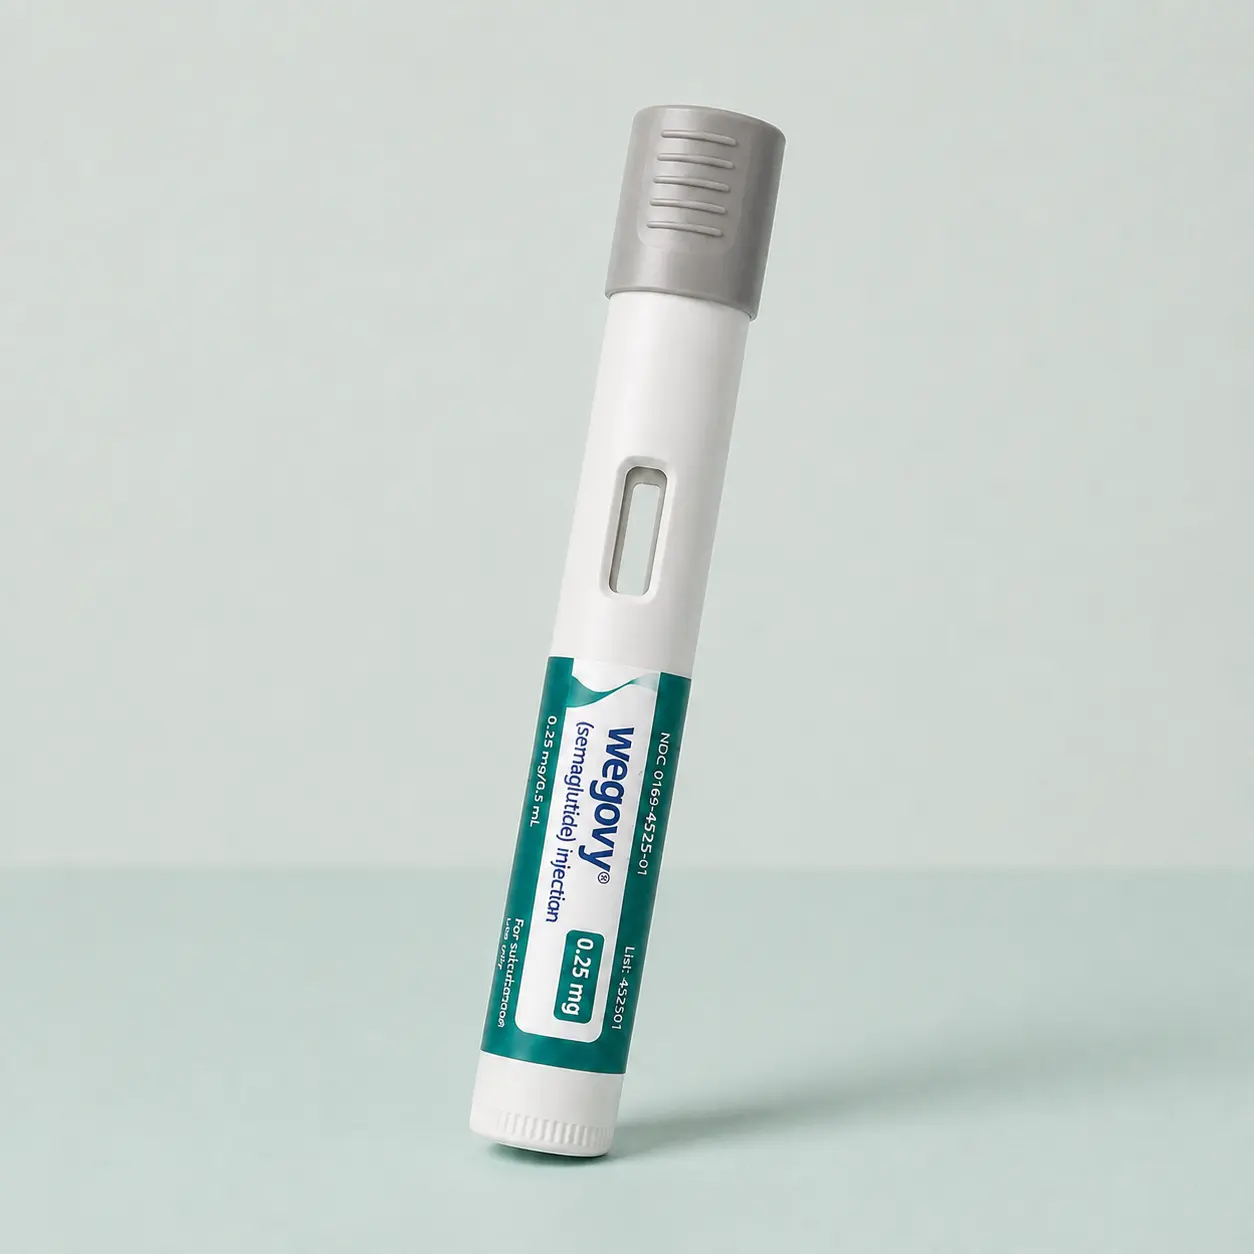
How Zappy treats it



Questions, answered
Do I qualify for medication?
Is it safe long term?
What happens if I stop?
Do you take insurance?
Keep reading
References
- STEP 1 — Wilding et al., NEJM 2021 (n=1,961): −14.9% at week 68 vs −2.4% placebo
- SURMOUNT-1 — Jastreboff et al., NEJM 2022 (n=2,539): −20.9% at 72 weeks (15 mg) vs −3.1% placebo
- SELECT — Lincoff et al., NEJM 2023 (n=17,604): 20% relative MACE reduction
- STEP 4 — Rubino et al., JAMA 2021: regain after discontinuation