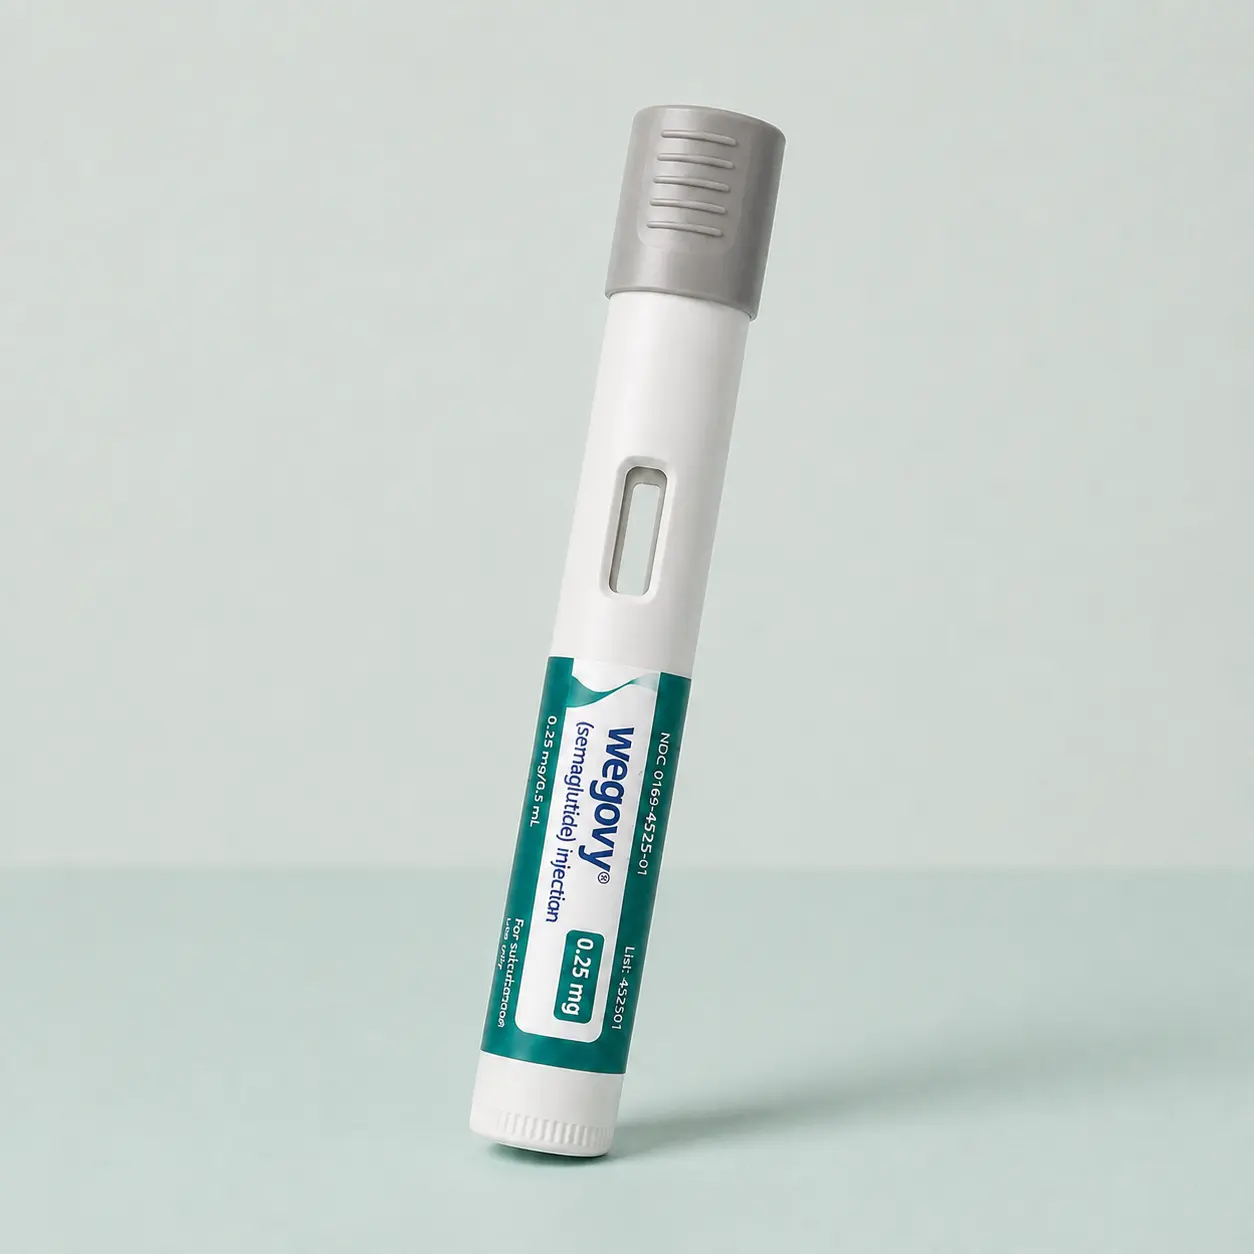
Position first, because the rest of this guide defends it: GLP-1 medications produce 14.9–20.9% average weight loss at full dose in randomized trials, semaglutide cuts cardiovascular events in people with heart disease, and the loss holds while you stay on the drug — stopping without a maintenance plan usually reverses it. The effect is rented, not owned. So the right frame is long-term therapy — with a protein target, resistance training, and a maintenance plan attached — not a 12-week kickstart.
Where the evidence is strong, we state it flatly. Where it is thin, we say so. Here is where everything sits.
A meal hormone, stretched to a week
GLP-1 (glucagon-like peptide-1) is a hormone your gut releases after eating. It does three things: slows gastric emptying, prompts the pancreas to release insulin when glucose rises, and signals fullness to appetite circuits in the hypothalamus and hindbrain. The natural hormone lasts minutes. Semaglutide and tirzepatide are engineered mimics that resist breakdown, so one injection covers seven days of continuous signaling. Tirzepatide adds a second action: agonism at the GIP receptor, a related gut-hormone pathway.
Two everyday experiences follow directly from that mechanism.
The quiet. Hunger, craving, and the background pull toward food recede — the effect often described as “food noise” going silent. That is the appetite-circuit action, felt from the inside.
The nausea. Food sitting longer in your stomach is precisely what slowed gastric emptying means, and each dose increase slows it further before your gut adapts. That is why nausea tracks dose escalation and fades as titration slows. Managing it is covered below.
Semaglutide: the molecule with a heart trial behind it
Semaglutide 2.4 mg weekly is the molecule in Wegovy (the same molecule, at different doses, is Ozempic for type 2 diabetes). Its pivotal trial is STEP 1 (Wilding et al., NEJM 2021): 1,961 adults with obesity and no diabetes, randomized to weekly semaglutide or placebo. At week 68, the semaglutide group had lost 14.9% of body weight on average. Placebo: 2.4%. Nausea was the most common side effect, and it clustered during dose escalation.
Then came the trial that changed what this class is for. SELECT (Lincoff et al., NEJM 2023) enrolled 17,604 adults with overweight or obesity and established cardiovascular disease — again, no diabetes — and counted major adverse cardiovascular events: heart attack, stroke, or death from cardiovascular causes. Semaglutide 2.4 mg reduced those events by 20% (hazard ratio 0.80) — a relative reduction, so your absolute benefit scales with your baseline risk.
Seventeen thousand people is outcome-trial scale. As of this guide’s last review, no other weight-loss medication has published comparable cardiovascular outcome evidence in people without diabetes. When heart disease is part of your history, this asymmetry should decide the molecule.
Tirzepatide: the bigger weight numbers
Tirzepatide is the molecule in Zepbound (Mounjaro at diabetes dosing) — the one that adds GIP agonism. In SURMOUNT-1 (Jastreboff et al., NEJM 2022), 2,539 adults spent 72 weeks on one of three doses or placebo. The dose–response came out clean: −15.0% at 5 mg, −19.5% at 10 mg, −20.9% at 15 mg. Placebo: −3.1%.
Read that against STEP 1 carefully. Even tirzepatide’s lowest dose matched full-dose semaglutide (15.0% vs 14.9%), and its top dose beat it by six percentage points. But these numbers come from different trials in different populations — treat the gap as directional, not exact.
What tirzepatide does not yet have is a published cardiovascular outcomes trial in this population to answer SELECT. The evidence is lopsided in both directions at once: tirzepatide leads on weight loss, semaglutide leads on proven cardiovascular outcomes. Pretending they are tied on both axes would be tidier, and wrong.
How we choose between them
Cardiovascular disease in your history: semaglutide, because outcome data beats extrapolation. Maximum weight loss as the goal, with an otherwise clean history: tirzepatide, because 20.9% beats 14.9%. Cost, availability, and your own side-effect history break the ties — a call to make with your clinician, case by case.
The dose-by-dose comparison lives here: semaglutide vs tirzepatide.
The first 16 weeks are a ramp, not a verdict
Standard semaglutide titration starts at 0.25 mg weekly and steps up roughly every 4 weeks — 0.25 → 0.5 → 1.0 → 1.7 → 2.4 mg — slower whenever side effects say so. The 0.25 mg start is a tolerability dose, not a treatment dose. It exists to let your gut adapt to slower emptying.
Judge the drug at your maintenance dose, not in week three. Deciding “it isn’t working” at 0.5 mg is deciding before the treatment has started.
Expect nausea to track the ramp. In STEP 1 it was the most common side effect and clustered during dose escalation — exactly what the mechanism predicts. If a step up bites, the fix is holding the current dose longer, not white-knuckling through. That is a clinician’s call: at Zappy, a US-licensed clinician reviews every case and adjusts the titration, and slowing the ramp is routine, not failure.
What to do during the ramp — clinical advice, not trial data: keep water intake high. Hold your protein floor (numbers in the next section). Favor several short walks over one long one; it often helps the nausea. And hand your clinician a complete list of your oral medications, because slower gastric emptying can change how quickly other drugs absorb, and timing adjustments are individual.
Some of what you lose is muscle
DXA substudies of the GLP-1 trials — body-composition scans run on a subset of participants — show that a meaningful fraction of the weight lost is lean mass, not fat. Keep the two tiers of this evidence separate.
What’s known: the lean-mass loss shows up on the scans, consistently enough to plan around.
What isn’t: long-term functional outcomes. Whether that lean-mass loss translates into weakness, frailty, or fracture risk years out has not been characterized. We don’t know.
The countermeasure is standard and low-regret: resistance training, plus protein at 1.2–1.6 g/kg of body weight per day — the range clinicians commonly target. For a 90 kg (198 lb) person, that is 108–144 g of protein daily, which does not happen by accident on a suppressed appetite. It has to be scheduled like a medication.
What happens when you stop
Two trials answer this directly, and they agree.
STEP 4 (Rubino et al., JAMA 2021): every participant took semaglutide for 20 weeks, then some continued and the rest switched to placebo. The continuers held their loss. The switchers substantially regained. The weight loss is maintained by staying on the drug.
SURMOUNT-4 (Aronne et al., JAMA 2024) ran the harder version with tirzepatide: 36 weeks on drug, then randomization. Over the following year, those switched to placebo regained about 14% of body weight. Those who stayed on lost roughly 5.5% more.
The conclusion is not subtle. Discontinuation without a maintenance plan usually reverses the loss.
Our clinical position — labeled as opinion, not trial data: start these drugs with a long-term frame. Budget for years, not months. Build the protein and training habits during treatment, because they are the only part of the intervention you keep for free if you ever stop. And here is what would change our position: a trial showing a discontinuation strategy that preserves the loss. Neither STEP 4 nor SURMOUNT-4 tested one — both switched to placebo outright, with no taper arm.
Branded or compounded: the honest version
If your insurance covers Wegovy or Zepbound, take the branded product. That advice runs against our commercial interest, and it is still the correct default.
If you are paying cash, compounded semaglutide and tirzepatide are prepared by LegitScript-verified 503A pharmacies in the US. Hold two facts at once, both stated plainly: compounded preparations are not FDA-approved — the compounded product itself has not gone through FDA review — and every Zappy case is reviewed by a US-licensed clinician who sets and adjusts your titration. No insurance is required at any step, and FSA/HSA funds are eligible.
Whether you qualify at all — weight thresholds, contraindications, interactions with what you already take — is a screening question, not a blog question: see if you qualify.
The short version
Evidence (randomized trials): semaglutide 2.4 mg averages 14.9% loss at 68 weeks (STEP 1); tirzepatide averages 15.0–20.9% by dose at 72 weeks (SURMOUNT-1); semaglutide cuts major cardiovascular events by 20% relative in people with existing heart disease (SELECT); stopping either drug brings substantial regain (STEP 4, SURMOUNT-4).
Consensus practice: titrate slowly — semaglutide 0.25 to 2.4 mg over roughly 16 weeks, slower with side effects — and protect lean mass with 1.2–1.6 g/kg/day of protein plus resistance training.
Our opinion: frame it as long-term therapy from day one; branded if insured, 503A compounded if cash-pay; judge the drug at maintenance dose, not during the ramp.
The trial we’re waiting for
The off-ramp. STEP 4 and SURMOUNT-4 tested one exit — abrupt switch to placebo — and both found regain. Neither tested a taper, a lower maintenance dose, intermittent dosing, or an intensive lifestyle bridge timed to discontinuation. So the obvious question — “am I on this forever?” — has no trial-grade answer yet. The honest current answer: the loss persists while you are on the drug, and the trials we have do not show a proven way off.
We are watching for two results: a discontinuation-strategy trial, and long-term functional data on the lean-mass question — the scan changes are documented, the strength and frailty outcomes are not. When either lands, this guide changes.